


Considerations
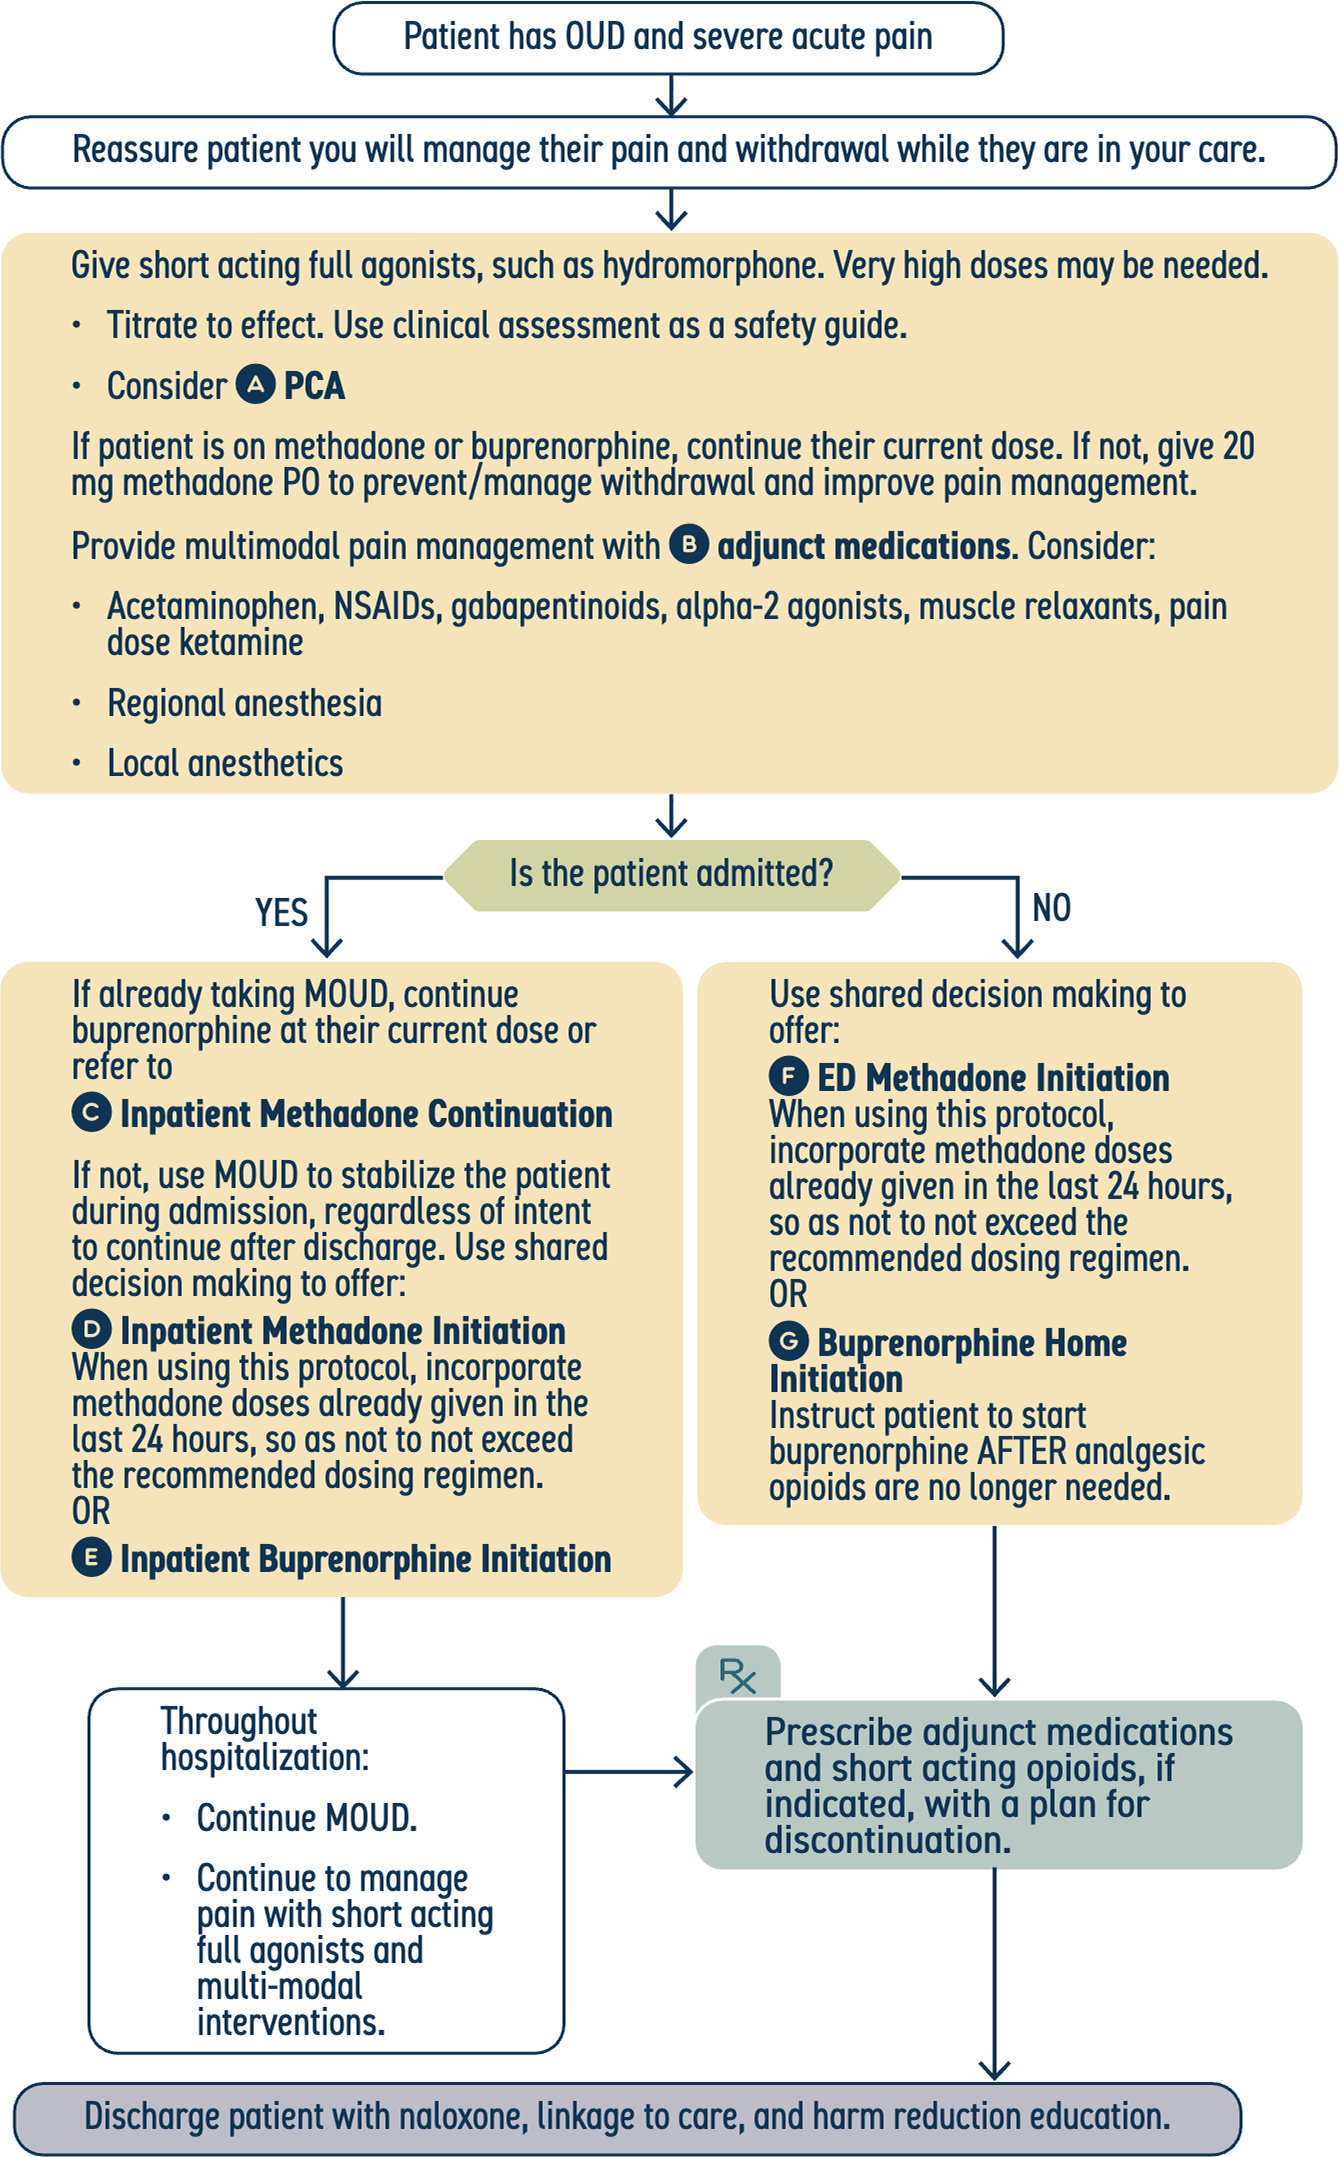
MOUD combined with short-acting opioids is recommended for severe acute pain in patients with OUD. MOUD stabilizes opioid receptors, making pain management easier.
Ensure pain and OUD symptoms are well controlled. Undertreatment drives patient-directed discharge, interrupting needed medical care and increasing risk of repeat ED visits/ admissions, return to use, and overdose.
Short acting, full agonist opioids:
- Can be used safely in combination with methadone and buprenorphine, with appropriate monitoring.
- May be needed at significantly higher than typical doses due to tolerance and hyperalgesia. See Opioid Dosing for Acute Pain in Patients with OUD and High Opioid Tolerance.
This protocol is appropriate for use in pregnant and lactating patients but is not comprehensive for pain management in labor and delivery.
This protocol does not cover the care of patients on naltrexone
See Additional Clinical Guidance for more information

Additional Clinical Guidance
- Acute pain in patients with OUD is treatable and should be actively managed.
- MOUD (methadone or buprenorphine) is used to stabilize OUD and should be maintained/initiated as soon as possible during an acute pain episode.
- Provide MOUD to stabilize the patient regardless of patient intent to continue it after discharge.
- Short-acting full agonist opioids, such as hydromorphone, are used in addition to MOUD to manage severe acute pain.
- Treating acute pain with opioids, when indicated, does not worsen OUD.
- Discussion of ongoing MOUD treatment options is more effective when pain and withdrawal are well-managed.
- Patients experience significant anxiety about pain.
- A caring, supportive approach is essential.
- Create a plan with the patient for what to do if their pain is not well controlled.
- Stigma against people with OUD prevents help-seeking.
- Challenge biases to provide compassionate, evidence-based care.
- Use non-stigmatizing, person-first language and trauma-informed care to promote engagement and improve outcomes.
- When possible, connect patients with peer support to improve engagement.
Assessment
- Reassess pain frequently.
- Monitoring for opioid safety
- Monitor SpO2 and respiratory rate (RR). Interpret in conjunction with level of consciousness, work of breathing, and overall clinical status.
- RR >12: generally safe to continue opioids.
- RR 10-11: acceptable if overall clinical status is reassuring.
- RR <10 or SpO2 <92%: hold opioids until improved; consider resuming at a lower dose or extended interval.
- RR <8: give naloxone 0.04 mg IV every 4 minutes until RR >10.
- If SpO2 <95% with normal RR, evaluate clinical status and comorbidities.
- Chronically hypoxic patients require individualized pain management with close monitoring of oxygenation.
- Sedation
- Sedation alone should not determine opioid toxicity in opioid-tolerant patients; include the full assessment described above
- Stimulant withdrawal, for example, can cause sedation and hypersomnia that mimics opioid over-sedation.
- When the full assessment is reassuring, opioids should not be withheld from a patient in pain whose sedation may be attributable to stimulant withdrawal or other factors.
- Monitor SpO2 and respiratory rate (RR). Interpret in conjunction with level of consciousness, work of breathing, and overall clinical status.
- Assess for other substance use; address other use disorders and withdrawal syndromes.
Labs
- Urine drug screening (UDS) is not needed to initiate treatment for OUD.
- UDS only indicates whether certain substances or their byproducts are present within a set detection window. It does not measure impairment, gauge severity of SUD, explain behavior, or rule out significant use when negative. It works best when it answers a specific clinical question and is part of a broader treatment plan.
- If UDS is performed for clinical reasons, obtain informed consent.
Pharmacotherapy
- Providing MOUD (buprenorphine, methadone) and short-acting full agonist opioids in combination is recommended to treat severe acute pain in patients with OUD.
- MOUD provides baseline opioid receptor stability that makes acute pain significantly easier to manage.
- Patients with OUD have altered central pain processing and receptor regulation that lowers pain tolerance and increases opioid requirements; MOUD corrects this.
- Withholding or delaying MOUD during an acute pain episode worsens pain control by compounding acute pain with withdrawal.
- MOUD can be understood as basal analgesia, analogous to long-acting insulin in a patient with Type 1 diabetes: it maintains physiologic stability but is not designed to address acute, high-intensity pain. Short-acting opioids serve as the bolus component, addressing breakthrough pain.
- Methadone is a full opioid agonist. It does not block receptors, thus short-acting opioids will bind freely.
- Buprenorphine is a partial opioid agonist. It partially blocks receptors, thus short-acting opioids will NOT bind freely; they will need to be administered at higher doses to compete with buprenorphine to provide analgesia.
- It is safe to initiate buprenorphine after methadone is administered using this protocol, and to continue methadone as the full agonist in the linked Inpatient Buprenorphine Initiation protocol.
- Precipitated withdrawal is a risk for patients who are chronically using methadone and then abruptly start buprenorphine, rather than gradually uptitrate it.
- The uptitration method for initiating buprenorphine creates a "ramp" onto buprenorphine over several days, rather than abrupt receptor activity change. This allows other opioids, including short term use of methadone, to occupy the receptors during buprenorphine initiation.
Pathophysiology
- Treating acute pain with opioids, when indicated, does not worsen OUD.
Special populations
- Pregnancy and lactation:
- This protocol is appropriate for use in pregnant and lactating patients but is not comprehensive for pain management in labor and delivery.
- A pain management plan should be created with the patient and other specialists as needed.
- Consider regional anesthesia for perioperative pain management in patients that undergo cesarean section.
- Extra care should be taken to prevent opioid withdrawal in pregnancy.
- Severe withdrawal requires urgent treatment.
- Withdrawal impacts placental function and increases the risk of stunted growth, preterm labor, and fetal distress, convulsions, and death.
- Methadone and buprenorphine are the gold standard of care for OUD in pregnancy.
- These medications greatly reduce risk of morbidity/mortality and pregnancy/delivery complications.
- See Medications for OUD in Pregnancy & Postpartum for more information.
- Refer to prenatal care.
- Encourage regular prenatal care for improved pregnancy/delivery outcomes.
- Encourage patients to discuss MOUD with their prenatal care provider. They can help the patient plan for the birth and postpartum period, including pain management and neonatal opioid withdrawal.
- Inform that changes in opioid tolerance, particularly in the postpartum period, can increase the risk of overdose.
- This protocol is appropriate for use in pregnant and lactating patients but is not comprehensive for pain management in labor and delivery.
- Adolescents: consider expert consultation for pain management.
- Consent: In Washington State, youth age 13+ can consent to OUD treatment (including methadone) without parental consent (RCW 71.34.530).
- Buprenorphine or methadone can be used for OUD stabilization/withdrawal management even if the patient does not intend to continue it after hospitalization.
- For ongoing OUD treatment after discharge:
- Consider whether buprenorphine or methadone is a better fit using shared decision making.
- Youth-specific methadone data is limited.
- Many OTPs are not well-equipped to provide care for youth. If considering methadone, confirm there is an accessible OTP that serves youth and can accept the patient before discharge.
Polysubstance use
- Polysubstance use is not a contraindication to MOUD.
- Stimulant use
- Stimulant withdrawal can cause sedation and hypersomnia that may be confused with over-sedation from opioids. See Assessment.
- Stimulant intoxication can mimic symptoms of opioid withdrawal, including dilated pupils, sweating, agitation, hypertension, tachycardia. Symptoms specific to opioid withdrawal include runny nose, yawning, and piloerection.
- Address withdrawal syndromes and other use disorders.
- Benzodiazepine and alcohol withdrawal must be monitored carefully and treated aggressively.
- Increase monitoring if treating withdrawal syndromes with other CNS depressants.
- Opioids do not treat other withdrawal syndromes.
Patient safety
- Undertreated pain and OUD symptoms are a well-recognized driver of patient-directed discharge and return to extra-medical opioid use, which carries greater risk to the patient than medically managing pain and OUD.
- The risk of respiratory depression is lower in patients without cardiopulmonary co-morbidities, younger age, and/or high opioid tolerance (daily fentanyl use) compared to lower tolerance or opioid-naïve patients, but respiratory rate should be monitored. See Assessment.
- Use caution and increase monitoring when initiating or increasing doses of other sedating medications.
Discharge planning
- Discharge with a plan for ongoing pain management.
- Provide prescriptions, including adjunct medications and short-acting opioids, if needed, with appropriate counseling and a plan for discontinuation and close follow up.
- Ensure the patient is discharged with naloxone in hand.
Patient Education
- Counsel on goals and expectations for pain management, including:
- The goal of pain management is not to eliminate pain entirely, but to achieve a level of comfort that allows them to meet functional goals (ambulation, deep breathing, participation in physical therapy, etc.).
- Discuss ongoing pain management strategies after discharge, such as over-the-counter medications and non-pharmacologic interventions.
- Continue taking MOUD as prescribed, even after pain has fully resolved.
- Educate on overdose prevention strategies (see Discharge Instructions).
- Emphasize that changes in opioid tolerance can increase the risk of overdose.
- Ensure the patient and their support system understand when and how to use naloxone.
Linkage to Care
- If applicable, refer the patient back to their established MOUD provider. Otherwise, help them schedule a follow up appointment.
- Hospitals enrolled in ScalaNW can call the 24/7 appointment scheduling line and receive a confirmed date, time, and location for MOUD follow up appointment during the 10-minute phone call.
- Hospitals not enrolled in ScalaNW may contact known sites directly or use the Washington Recovery Helpline.
- Ensure the patient is aware of the date, time and location for follow up.
- When possible, connect patients with social work, care navigation, and/or peer support to strengthen linkage to care.
- If possible, obtain an ROI to coordinate care and send the discharge summary.
Discharge Instructions
Medication Information
- Continue taking medications to treat opioid use disorder, even after your pain improves.
- It is common for people on medications for opioid use disorder to need additional medications when they have severe pain.
- Take pain medications as prescribed. If you were given a prescription, fill it as soon as possible so you have it when you need it.
- Do not take more than the recommended dose of any medication.
- If you are taking over-the-counter pain relievers such as ibuprofen or acetaminophen, follow the dosing instructions on the label.
- Do not combine products that contain the same active ingredient.
- Tell your provider that you have a painful condition and what medications you were prescribed today.
Overdose Prevention
Using street drugs is risky. If you do use, reduce your risk of dying from an opioid overdose with the following:
- Naloxone (Narcan)
- Today you received naloxone or a prescription for naloxone. This is an opioid overdose reversal medication. It is safe to use on anyone you suspect is experiencing an opioid overdose.
- Visit stopoverdose.org or talk to your provider, nurse, or pharmacist to learn more.
- Try not to use alone
- If plan to use alone, call SafeSpot at 1-800-972-0590. SafeSpot is a 24/7, peer-led overdose detection and prevention hotline. They will send someone to help if you stop responding during a phone call.
- Start low & go slow
- You can't know the complete contents or strength of street drugs. If you plan to use, start with a small amount to see how it affects you. If you have low tolerance (such as after a period of not using), be extra cautious. If you decide to use more, slowly increase by using small amounts at a time.
- Watch and wait before next person uses
- If you’re with a group of people, take turns to see how the product is affecting people. Someone needs to be able to ask for help, if it’s needed.
- Avoid mixing drugs
- Mixing drugs increases your risk. If you do use multiple drugs, try to use one at a time and use less of each.
- Know the signs of opioid overdose and how to respond.
- If someone is unresponsive or has unusual or no breathing, call 911 and give them naloxone and rescue breaths.
- Always have naloxone
- Tell others you have it, where it is, when to use it.
- Treatment with methadone or buprenorphine
- These medications, if taken as directed, reduce the risk of death by over 50%.
- If you need help finding a treatment provider, call the Washington Recovery Helpline at 866-789-1511 or go to warecoveryhelpline.org.
- You can also start buprenorphine or get an urgent prescription with a phone visit by calling the WA Telebuprenorphine line at (206) 289-0287. Learn more at WAtelebupe.org.
 Copy Discharge Instructions
Additional Resources
- U.S. Department of Health and Human Services 2019 Pain Management Best Practices Inter-Agency Task Force Report
- UW Pain & Opioid Provider Hotline 844-520-7246: gives free on-demand clinical and case-based advice to healthcare providers caring for patients with complex pain medication regimens, especially high-dose opioids.
References
- American Psychiatric Association. Treatment of opioid use disorder in the general hospital. Approved by the Joint Reference Committee, October 2022. American Psychiatric Association; 2022:59. https://www.psychiatry.org/getattachment/879082d5-af6b-4c26-86e5-152bd53012b5/Resource-Document-Treatment-of-OUD-in-General-Hospital.pdf
- Cobb J, Craig W, Richard J, et al. A Retrospective Study of Acute Postoperative Pain After Cesarean Delivery in Patients With Opioid Use Disorder Treated With Opioid Agonist Pharmacotherapy. J Addict Med. 2022;16(5):549-556. doi:10.1097/ADM.0000000000000964
- Crotty K, Freedman KI, Kampman KM. Executive summary of the focused update of the ASAM National Practice Guideline for the treatment of opioid use disorder. J Addict Med. 2020;14(2):99-112. doi:10.1097/ADM.0000000000000635
- De Aquino JP, Parida S, Avila-Quintero VJ, et al. Opioid-induced analgesia among persons with opioid use disorder receiving methadone or buprenorphine: A systematic review of experimental pain studies. Drug Alcohol Depend. 2021;228:109097. doi:10.1016/j.drugalcdep.2021.109097
- Englander H, Thakrar AP, Bagley SM, Rolley T, Dong K, Hyshka E. Caring for hospitalized adults with opioid use disorder in the era of fentanyl: a review. JAMA Intern Med. 2024;184(6):691-701. doi:10.1001/jamainternmed.2023.7282
- Greenwald MK, Comer SD, Fiellin DA. Buprenorphine maintenance and mu-opioid receptor availability in the treatment of opioid use disorder: implications for clinical use and policy. Drug Alcohol Depend. 2014;144:1-11. doi:10.1016/j.drugalcdep.2014.07.035
- Kampman K, Jarvis M. American Society of Addiction Medicine (ASAM) National Practice Guideline for the Use of Medications in the Treatment of Addiction Involving Opioid Use. J Addict Med. 2015;9(5):358-367. doi:10.1097/ADM.0000000000000166
- Merlin JS, Khodyakov D, Arnold R, et al. Expert Panel Consensus on Management of Advanced Cancer-Related Pain in Individuals With Opioid Use Disorder. JAMA Netw Open. 2021;4(12):e2139968. Published 2021 Dec 1. doi:10.1001/jamanetworkopen.2021.39968
- Nagpal AK, Gadkari C, Singh A, Pundkar A. Optimizing Pain Management in Emergency Departments: A Comprehensive Review of Current Analgesic Practices. Cureus. 2024;16(9):e69789. Published 2024 Sep 20. Doi:10.7759/cureus.69789
- Polomano, R. C., Fillman, M., Giordano, N. A., Vallerand, A. H., Nicely, K. L., & Jungquist, C. R. (2017). Multimodal Analgesia for Acute Postoperative and Trauma-Related Pain. The American journal of nursing, 117(3 Suppl 1), S12–S26. https://doi.org/10.1097/01.NAJ.0000513527.71934.73
- Simon R, Snow R, Wakeman S. Understanding why patients with substance use disorders leave the hospital against medical advice: A qualitative study. Subst Abus. 2020;41(4):519-525. doi:10.1080/08897077.2019.1671942
- Thakrar AP, Lowenstein M, Greysen SR, Delgado MK. Trends in Before Medically Advised Discharges for Patients With Opioid Use Disorder, 2016-2020. JAMA. 2023;330(23):2302-2304. doi:10.1001/jama.2023.21288
- Varrassi G, Farì G, Narvaez Tamayo MA, et al. Mixed pain: clinical practice recommendations. Front Med (Lausanne). 2025;12:1659490. Published 2025 Oct 9. Doi:10.3389/fmed.2025.1659490
- U.S. Department of Health and Human Services (2019, May). Pain Management Best Practices Inter-Agency Task Force Report: Updates, Gaps, Inconsistencies, and Recommendations. Retrieved from U. S. Department of Health and Human Services website: https://www.hhs.gov/ash/advisory-committees/pain/reports/index.html
- Veazie S, Mackey K, Peterson K, Bourne D. Managing Acute Pain in Patients Taking Medication for Opioid Use Disorder: a Rapid Review. J Gen Intern Med. 2020;35(Suppl 3):945-953. doi:10.1007/s11606-020-06256-5
- Xu J, Liu X, Zhao J, et al. Comprehensive Review on Personalized Pain Assessment and Multimodal Interventions for Postoperative Recovery Optimization. J Pain Res. 2025;18:2791-2804. Published 2025 Jun 5. doi:10.2147/JPR.S516249


