


Considerations
Interpret SpO2 and respiratory rate with level of consciousness, work of breathing, and overall clinical status
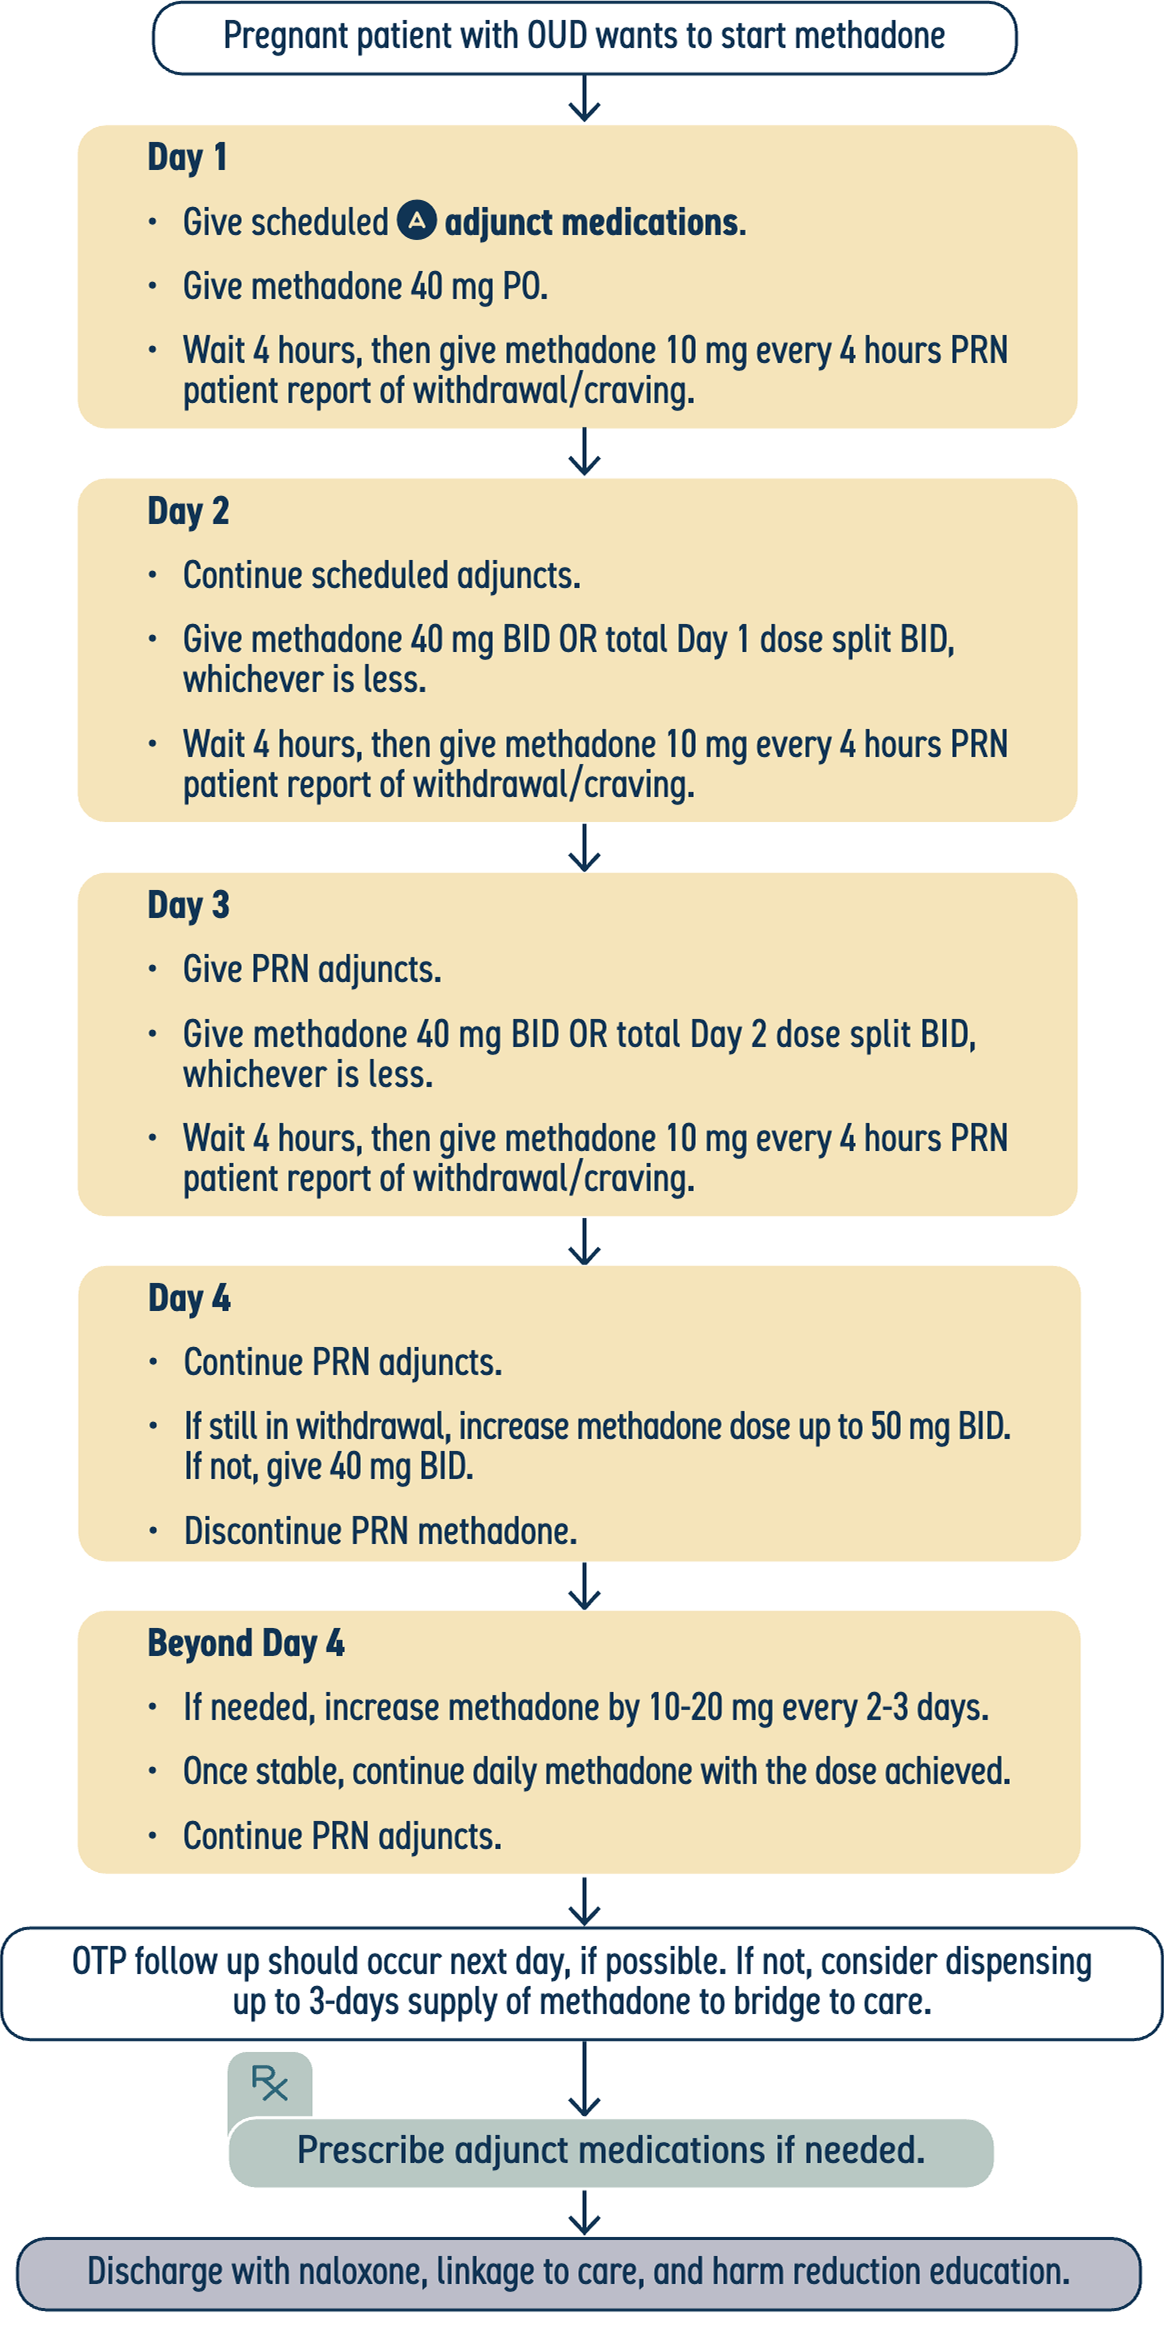
Methadone for OUD greatly reduces risk of overdose and pregnancy/ delivery complications.
Severe withdrawal can harm the pregnancy/fetus and requires urgent treatment with short acting opioids.
Review drug-drug interactions before starting methadone.
Consider ECG monitoring for: COPD with O2 required, heart disease, ESRD, cirrhosis. Do not delay methadone to obtain ECG.
Consider 30 mg starting dose and slower escalation if: any of the above comorbidities, lower tolerance, methadone naïve, concurrent sedative use
This rapid dose escalation is safe with inpatient monitoring and gets patients closer to a therapeutic dose before discharge, reducing overdose risk.
Assess ability to establish OTP care; if not, consider buprenorphine.
See Additional Clinical Guidance for more information.

Additional Clinical Guidance
- Opioid use disorder (OUD) is treatable.
- Methadone for OUD reduces the risk of death by over 50%.
- Methadone is a gold standard treatment for OUD in pregnancy and improves outcomes for the dyad. It is recommended by the American College of Obstetricians and Gynecologists (ACOG).
- Adjust dosing to minimize or eliminate withdrawal and opioid craving.
- The rapid dose escalation used in this protocol is safe in observed settings with respiratory rate monitoring, split dosing, and PRN dosing.
- BID dosing is needed in pregnancy due to metabolic changes.
- Recovery commonly requires multiple treatment attempts.
- Swiftly and adequately manage withdrawal and OUD symptoms.
- Poor symptom management commonly results in patient-directed discharge, interrupting needed medical care and increasing risk of repeat admission, return to use, and overdose.
- Withdrawal may cause fetal distress and increases risk of preterm labor and other pregnancy and delivery complications.
- Risk of neonatal opioid withdrawal syndrome (NOWS) should not discourage methadone.
- NOWS is an expected and treatable outcome for neonates chronically exposed to opioids in utero, including extra-medical and prescribed opioids.
- See Medications for OUD in Pregnancy & Postpartum for more information.
- Stigma against pregnant people with OUD prevents help-seeking and prenatal care.
- Challenge biases to provide compassionate, evidence-based care.
- Use non-stigmatizing, person-first language and trauma-informed care to promote engagement and improve outcomes.
- Substance use should not be conflated with child abuse/neglect. In Washington state, substance use alone does not constitute a mandatory report to Child Protective Services.
- When possible, connect patients with peer support to improve engagement.
- For complex cases, consult the Perinatal Psychiatry Consultation Line
- Available Monday- Friday (closed holidays), 9 AM-5 PM
- 877-725-4666, ppcl@uw.edu
Assessment
- Assess for considerations to use a lower (30 mg) starting dose and slower dose escalation:
- Comorbid cardiac disease, severe pulmonary disease, ESRD, or cirrhosis.
- Lower opioid tolerance. Tolerance may be lower if the patient:
- Does not need to use fentanyl multiple times daily to prevent/manage withdrawal.
- Is using an opioid that is less potent than fentanyl (e.g., oxycodone).
- Methadone-naïve. If the patient has never been on methadone, increased caution is warranted.
- Concurrent sedative use.
- Monitor for patient-reported opioid craving and withdrawal symptoms.
- PRN methadone should be offered based on the patient's self-report of either withdrawal symptoms and/or cravings to use opioids.
- A Clinical Opiate Withdrawal Scale (COWS) score is not recommended as a prerequisite for PRN methadone.
- The COWS was designed to measure opioid withdrawal severity; it was not validated to determine when PRN methadone dosing is appropriate during methadone initiation.
- The clinical goal during methadone titration is to treat the full spectrum of OUD symptoms, including cravings and subjective withdrawal, not only measurable withdrawal.
- Despite this, some clinicians have a strong preference for guiding assessment with an objective tool. In this case, a COWS of 4+ may be used to confirm appropriateness of a PRN methadone, but a low COWS score should not be used to withhold a PRN dose from a patient who reports cravings or subjective withdrawal.
- Monitoring for opioid safety
- Monitor SpO2 and respiratory rate (RR). Interpret in conjunction with level of consciousness, work of breathing, and overall clinical status.
- RR >12: generally safe to continue.
- RR 10-11: acceptable if overall clinical status is reassuring.
- RR <10 or SpO2 <92%: hold doses until improved; consider resuming at a lower dose or extended interval.
- RR <8: give naloxone 0.04 mg IV q4min until RR >10.
- If SpO2 <95% with normal RR, evaluate clinical status and comorbidities.
- Chronically hypoxic patients require individualized pain management with close monitoring of oxygenation.
- Monitor SpO2 and respiratory rate (RR). Interpret in conjunction with level of consciousness, work of breathing, and overall clinical status.
- Sedation
- Sedation alone should not determine opioid toxicity in opioid-tolerant patients; include the full assessment described above
- Stimulant withdrawal, for example, can cause sedation and hypersomnia that mimics opioid over-sedation.
- When the full assessment is reassuring, opioids should not be withheld from a patient in pain whose sedation may be attributable to stimulant withdrawal or other factors.
- ECG 12-lead for QTc monitoring
- Patients with risk factors (e.g., heart disease, use of other QTc-prolongating medications, history of prolonged QTc) should receive an ECG.
- Consider a baseline ECG for any patient initiating methadone.
- Do not delay treatment to obtain an ECG.
- Assess patient ability to connect with an opioid treatment program (OTP).
- Ongoing dispensing of methadone for OUD can only be provided by an OTP.
- Consider proximity, transportation, and OTP requirements (e.g., frequency of in person dosing).
- If ongoing treatment with methadone is not feasible, offer buprenorphine instead.
- If ongoing treatment plan is undecided, methadone or buprenorphine can be used to stabilize OUD while the patient is admitted. MOUD should be provided regardless of intent to continue it after discharge.
- Assess for and address other use disorders and withdrawal syndromes.
- Consider screening for sexually transmitted infections, including HIV, hepatitis C, syphilis, gonorrhea, and chlamydia. Consider linkage to PrEP as indicated.
Pain considerations
- Ensure pain and OUD symptoms are adequately controlled to prevent patient-directed discharge.
- Patients experience significant anxiety about pain.
- A caring, supportive approach is essential.
- Create a plan with the patient for what to do if their pain is not well controlled.
- Discussion of MOUD treatment options is more effective when pain and withdrawal are well-managed.
- Provide multimodal pain management and maximize non-opioid pain interventions. Consider acetaminophen, gabapentinoids, alpha-2 agonists, muscle relaxants, local anesthetics, regional anesthesia, and nonpharmacologic approaches. See Adjunct Medications.
- Treat acute pain with opioids, when indicated.
- This does not worsen OUD.
- Patients with opioid tolerance may require significantly higher than usual dose of opioid analgesics to adequately control pain. See Opioid Dosing for Acute Pain in Patients with OUD and High Opioid Tolerance.
- There are no additional considerations for dose intervals between methadone and short acting opioids. Treat pain as indicated. There are no adjustments required related to methadone titration.
- Consider patient-controlled analgesia.
- When providing high doses or multiple formulations of opioids, monitor SpO2 and respiratory rate (RR). Interpret in conjunction with level of consciousness, work of breathing, and overall clinical status. See Assessment.
- These pain considerations are not comprehensive for labor and delivery. Consult appropriate specialties.
- Discharge with a plan for ongoing pain management. Provide prescriptions, including short-acting opioids if needed, with appropriate counseling and a plan for discontinuation.
Labs
- Urine drug screening (UDS) is not needed to initiate treatment for OUD.
- UDS only indicates whether certain substances or their byproducts are present within a set detection window. It does not measure impairment, gauge severity of SUD, explain behavior, or rule out significant use when negative. It works best when it answers a specific clinical question and is part of a broader treatment plan.
- False-positives and false-negatives are not uncommon.
- If UDS is performed for clinical reasons, obtain informed consent.
- A positive UDS should not be conflated with child abuse or neglect.
- Support the dyad by providing evidence-based treatment and patient education.
- In Washington state, substance use alone does not constitute a mandatory report to Child Protective Services.
Pharmacotherapy
- Methadone is a long-acting opioid agonist that treats opioid withdrawal and lessens cravings to use extra-medical opioids.
- Methadone can be used for acute withdrawal management, even if buprenorphine is preferred for ongoing treatment. It peaks within ~2-4 hours of dosing.
- Withdrawal management
- Patients commonly experience withdrawal while methadone is titrated to a therapeutic dose.
- Manage symptoms with adjunct medications.
- Early on, adjunct medications should be given scheduled. As patients stabilize, adjuncts can be given PRN.
- Continue to provide PRN adjunct medications throughout the stabilization process, including prescriptions on discharge, if needed.
- For severe withdrawal
- In addition to methadone, provide a short-acting opioid such as hydromorphone 4-8 mg PO every 3 hours PRN severe/breakthrough withdrawal. Hold for RR <12 and see Monitoring for opioid safety under Assessment, above.
- Provide on Days 1- 2 only, as priority should be given to rapid methadone dose escalation.
- Adjust dosing as needed to adequately manage symptoms while ensuring safety.
- Because methadone is long acting, doses accumulate by day 3 and 4 (known as “dose stacking”). If withdrawal is well managed without PRN doses on Day 3, do not increase the scheduled dose on Day 4, because of dose stacking and risk of over sedation.
- Higher doses than recommended on days 3 and 4 increase the risk of over-sedation but may be necessary if withdrawal remains severe.
- Split (BID) methadone dosing is strongly recommended as the standard of care in pregnancy due to metabolic changes. Split dosing also allows for a faster up-titration of methadone to resolve withdrawal and reach a therapeutic dose.
- Example dosing:
Day 1: Give methadone 40 mg PO. Wait 4 hours after initial dose, then give 10 mg methadone every 4 hours PRN patient report of withdrawal/craving. Hold for RR <12.
| Time | RR | Clinical Status | Action | Cumulative Dose |
|---|---|---|---|---|
| 0800 | 13 | Initiating methadone; scheduled dose administered | Methadone 40 mg PO (scheduled) | 40 mg |
| 1200 | 14 | Withdrawal reported, diaphoretic | Methadone 10 mg PO (PRN) | 50 mg |
| 1600 | 14 | GI symptoms | Methadone 10 mg PO (PRN) | 60 mg |
| 2000 | 13 | Opioid craving and restlessness | Methadone 10 mg PO (PRN) | 70 mg |
| 0000 | 12 | Resting comfortably | No dose given | 70 mg |
| Total | 70 mg | |||
Day 2: Give 40 mg BID, or total Day 1 dose spilt BID, whichever is less. Wait 4 hours after initial scheduled dose, then give 10 mg methadone every 4 hours PRN patient report of withdrawal/craving. Hold for RR <12.
| Time | RR | Clinical Status | Action | Cumulative Dose |
|---|---|---|---|---|
| 0800 | 14 | Scheduled dose due | Methadone 35 mg PO (scheduled) | 35 mg |
| 1200 | 14 | Withdrawal and craving reported | Methadone 10 mg PO (PRN) | 45 mg |
| 1600 | 12 | Craving | Methadone 10 mg PO (PRN) | 55 mg |
| 2000 | 13 | Scheduled dose due | Methadone 35 mg PO (scheduled; second BID dose) | 90 mg |
| 0000 | 11 | No withdrawal or craving reported | PRN held (RR < 12) | 90 mg |
| Total | 90 mg | |||
Pathophysiology
If a patient continues to use extra-medical opioids while on methadone, a higher dose may be indicated to better manage OUD symptoms. Continued substance use is not a reason to stop treatment or consider it a failure. Methadone significantly reduces the risk of all-cause mortality for people with OUD, even with continued extra-medical opioid use.
Special populations
- For more information on methadone in pregnancy, see Medications for OUD in Pregnancy & Postpartum.
- Adolescents:
- Consent: In Washington State, youth age 13+ can consent to OUD treatment (including methadone) without parental consent (RCW 71.34.530).
- For ongoing OUD treatment after discharge:
- Consider whether buprenorphine or methadone is a better fit using shared decision making.
- Youth-specific methadone data is limited.
- Many OTPs are not well-equipped to provide care for youth. If considering methadone for ongoing OUD treatment, confirm there is an accessible OTP that serves youth and can accept the patient before discharge.
Polysubstance use
- Polysubstance use is not a contraindication to methadone for OUD.
- Stimulant use
- Stimulant withdrawal can cause sedation and hypersomnia that may be confused with over-sedation from methadone. See Assessment.
- Stimulant intoxication can mimic symptoms of opioid withdrawal, including dilated pupils, sweating, agitation, hypertension, tachycardia. Symptoms specific to opioid withdrawal include runny nose, yawning, and piloerection.
- Address withdrawal syndromes and other use disorders.
- Benzodiazepine and alcohol withdrawal must be monitored carefully and treated aggressively.
- Increase monitoring and consider splitting methadone dose BID if treating withdrawal syndromes with other CNS depressants.
- Methadone does not treat other withdrawal syndromes.
Patient safety
- This protocol rapidly escalates methadone to achieve a therapeutic dose.
- This approach is safe in observed settings with the included safety parameters, including split dosing, waiting 4 hours between PRN doses (methadone’s peak effect is typically within 2-4 hours of dosing), and holding for low respiratory rate.
- Undertreated OUD symptoms are a well-recognized driver of patient-directed discharge and return to extra-medical opioid use, which carries greater risk to the patient and the pregnancy than medically managed, observed, rapid up titration of methadone.
- The risk of respiratory depression is lower in patients without cardiopulmonary co-morbidities, younger age, and/or high opioid tolerance (daily fentanyl use) compared to lower tolerance or opioid-naïve patients, but respiratory rate should be monitored. See Assessment.
- If withdrawal is well managed without PRN doses, do not increase the next day’s scheduled dose.
- Methadone is long acting; initial doses accumulate on days 3 and 4 (known as “dose stacking”). Increasing the dose when withdrawal symptoms are well managed the previous day risks over sedation.
- Use caution and increase monitoring when initiating or increasing doses of other sedating medications.
Discharge planning
- Dispensing methadone
- If dispensed methadone doses are needed to bridge to care (e.g., OTP is closed or unable to accommodate patient at time of next dose), coordinate prior to discharge.
- The facility must have a process must be in place prior to doing this. See Dispensing Methadone for Opioid Use Disorder Under the 72 Hour Rule for guidance.
- Prescribe adjunct medications for withdrawal, if needed.
- Patients commonly need adjunct medications to manage withdrawal symptoms until they stabilize on the medication.
- Prescription duration should be at least 7 days.
- Ensure the patient is discharged with naloxone in hand.
Patient education
- Methadone is a safe and effective treatment for opioid withdrawal and OUD in pregnancy. It helps people with OUD have a healthier pregnancy.
- The baby may experience neonatal opioid withdrawal syndrome (NOWS) shortly after delivery. This is expected when taking methadone, is treatable, and does not cause long-term health issues. It is much riskier to leave OUD untreated.
- Patients should be strongly encouraged to discuss their MOUD treatment with their OB provider to help them plan for labor, delivery, and postpartum, including pain and NOWS management.
- Methadone can cause respiratory depression and overdose when taken at higher than prescribed doses or when combined with other sedatives. Patients should not start or increase the use of extra-medical CNS depressants, including alcohol, while starting methadone.
- If discharging with dispensed methadone, ensure careful, comprehensive education on medication risks and appropriate dosing, including dosing at the same times each day and never combining doses.
- Educate on overdose prevention strategies (see Discharge Instructions).
- Emphasize that changes in opioid tolerance, particularly in the postpartum period, can increase the risk of overdose.
- Ensure the patient and their support system understand when and how to use naloxone.
Linkage to care
- When possible, connect patients with social work, care navigation, and/or peer support to strengthen linkage to care.
- Discuss available OTP options for ongoing care.
- Help the patient schedule an appointment or inform them of walk-in availability for OTP intake.
- Hospitals enrolled in ScalaNW can call the 24/7 appointment scheduling line and receive a confirmed date, time, and location for MOUD follow up appointment during the 10-minute phone call.
- Hospitals not enrolled in ScalaNW may contact known sites directly or use the Washington Recovery Helpline to find available OTPs.
- Ensure the patient is aware of the date, time and location for follow up.
- Prepare the patient for OTP follow up:
- Educate the patient on OTP expectations, which vary, but may initially include daily visits.
- The patient should tell the OTP that they were started on methadone in the hospital.
- Provide the patient with documentation of methadone doses provided, including the date, time, and amount of last dose. The OTP will call the hospital pharmacy to confirm last dose, but providing this documentation can prevent delays.
- If possible, obtain an ROI to coordinate with the receiving OTP. Send the discharge summary, including information on doses administered and bridge doses dispensed.
- Refer to prenatal care. Encourage regular prenatal care for improved pregnancy/delivery outcomes.
Discharge Instructions
- Information about methadone
- Methadone is a medication that treats opioid use disorder. It helps people end the cycle of use and withdrawal so they can feel stable. It also reduces the risk of opioid overdose and death.
- Side effects are usually mild and improve over time. They may include constipation, sweating, headache, dizziness, trouble sleeping, nausea, and sleepiness. Tell your healthcare provider if you have these symptoms.
- Caution:
- Combining methadone with other sedatives or “downers” can cause overdose. Don’t start or increase your normal amount of use of any “downers” (including alcohol, opioids like fentanyl, benzos like Xanax, and sleep or anxiety medications) while you get used to methadone.
- Methadone is an opioid. Suddenly stopping methadone can cause withdrawal.
- Methadone is safe in pregnancy and improves the health and safety of both you and your baby.
- Methadone can help you reduce or stop other opioid use (like fentanyl), and avoid withdrawal, which is safer for you and the baby.
- The baby may experience opioid withdrawal shortly after birth. This is expected, treatable, and does not cause long-term health issues.
- Talk to your prenatal care provider about your methadone treatment. They will help you plan for the birth and postpartum period, including managing your pain and the baby’s withdrawal.
Methadone is also safe in breastfeeding and can help reduce the baby’s withdrawal symptoms shortly after birth.
- Follow up care
- Follow up or establish care with a prenatal care provider. Getting regular prenatal care will help you have a healthier pregnancy and delivery.
- To stay on methadone, you must go to an opioid treatment program (OTP), also known as a methadone clinic.
- Go to the OTP as soon as possible after leaving the hospital, so you can get your next dose on time.
- Sign any needed paperwork to allow them to talk to the hospital. This will help make sure you get the right dose and any other needed follow up care.
| Follow up date/time: |
| Location: |
| Phone number: |
| Date/time of last dose: |
Overdose Prevention
Using street drugs is risky. If you do use, reduce your risk of dying from an opioid overdose with the following:
- Naloxone (Narcan)
- Today you received naloxone or a prescription for naloxone. This is an opioid overdose reversal medication. It is safe to use on anyone you suspect is experiencing an opioid overdose.
- Visit stopoverdose.org or talk to your provider, nurse, or pharmacist to learn more.
- Try not to use alone
- If plan to use alone, call SafeSpot at 1-800-972-0590. SafeSpot is a 24/7, peer-led overdose detection and prevention hotline. They will send someone to help if you stop responding during a phone call.
- Start low & go slow
- You can't know the complete contents or strength of street drugs. If you plan to use, start with a small amount to see how it affects you. If you have low tolerance (such as after a period of not using), be extra cautious. If you decide to use more, slowly increase by using small amounts at a time.
- Watch and wait before next person uses
- If you’re with a group of people, take turns to see how the product is affecting people. Someone needs to be able to ask for help, if it’s needed.
- Avoid mixing drugs
- Mixing drugs increases your risk. If you do use multiple drugs, try to use one at a time and use less of each.
- Know the signs of opioid overdose and how to respond.
- If someone is unresponsive or has unusual or no breathing, call 911 and give them naloxone and rescue breaths.
- Always have naloxone (Narcan)
- Tell others you have it, where it is, when to use it.
- Treatment with methadone or buprenorphine
- These medications, if taken as directed, reduce the risk of death by over 50%.
- If you need help finding a treatment provider, call the Washington Recovery Helpline at 866-789-1511 or go to warecoveryhelpline.org.
- You can also start buprenorphine or get an urgent prescription with a phone visit by calling the WA Telebuprenorphine line at (206) 289-0287. Learn more at WAtelebupe.org.
 Copy Discharge Instructions
Regulations
- Per 21 C.F.R. § 1306.07(c) and 42 C.F.R. § 8.11(h)(3), a patient with OUD who is admitted for a medical condition (including complications of substance use), may receive methadone during the inpatient stay to initiate, continue, or adjust maintenance treatment or manage withdrawal.
- Per 21 CFR 1306.07(b), patients may be dispensed a supply of up to 3 days of methadone to bridge the gap between discharge and OTP follow up.
Copy Regulations
Additional Resources
- Washington State Opioid Treatment Program Guide
- UW Pain & Opioid Provider Hotline - UW Anesthesiology & Pain Medicine
- Perinatal Psychiatry Consultation Line for Providers (Perinatal PCL): https://perc.psychiatry.uw.edu/perinatal-pcl/
- Contact: 877-725-4666, ppcl@uw.edu, available Monday- Friday (closed holidays), 9 AM-5 PM
- Academy of Perinatal Harm Reduction: https://www.perinatalharmreduction.org/
References
- American College of Obstetricians and Gynecologists. Statement of policy: Opposition to Criminalization of Individuals During Pregnancy and the Postpartum Period. Retrieved 5/4/2026 from https://www.acog.org/clinical-information/policy-and-position-statements/statements-of-policy/2020/opposition-criminalization-of-individuals-pregnancy-and-postpartum-period
- American Psychiatric Association. Treatment of opioid use disorder in the general hospital. Approved by the Joint Reference Committee, October 2022. American Psychiatric Association; 2022:59.
- American Society of Addiction Medicine. National practice guideline for the treatment of opioid use disorder 2020 focused update. American Society of Addiction Medicine; 2020.
- Babu KM, Brent J, Juurlink DN. Prevention of Opioid Overdose. N Engl J Med. 2019;380(23):2246-2255. doi:10.1056/NEJMra1807054
- Bogen DL, Perel JM, Helsel JC, et al. Pharmacologic evidence to support clinical decision making for peripartum methadone treatment. Psychopharmacology (Berl). 2013;225(2):441-451. doi:10.1007/s00213-012-2833-7
- Bosshardt Z, Ortega Perez M, Casarella J, Buresh M, Tang YL. Dosing and Safety of Methadone Initiation in the Setting of Fentanyl: A Systematic Review. J Addict Med. Published online December 11, 2025. doi:10.1097/ADM.0000000000001629
- Bowman LA, Berger O, Nesbit S, Stoller KB, Buresh M, Stewart R. Operationalizing the new DEA exception: A novel process for dispensing of methadone for opioid use disorder at discharge from acute care settings. Am J Health Syst Pharm. 2024;81(6):204-218. doi:10.1093/ajhp/zxad288
- Braun HM, Potee RA. Individualizing methadone treatment with split dosing: An underutilized tool. J Subst Use Addict Treat. 2023;152:209096. doi:10.1016/j.josat.2023.209096
- Bromley L, Kahan M, Regenstreif L, Srivastava A, Wyman J. Methadone treatment for people who use fentanyl: recommendations. META:PHI; 2021:30. www.metaphi.ca
- Casey S, Regan S, Gale E, et al. Rapid methadone induction in a general hospital setting: a retrospective, observational analysis. Subst Abuse. 2023;44(3):177-183. doi:10.1177/08897077231185655
- Chou R, Cruciani RA, Fiellin DA, et al. Methadone safety: a clinical practice guideline from the American Pain Society and College on Problems of Drug Dependence, in collaboration with the Heart Rhythm Society. J Pain. 2014;15(4):321-337. doi:10.1016/j.jpain.2014.01.494
- Cohen SM, Straus E, Fiellin DA, et al. Hospital-Based Methadone and Buprenorphine Initiation Practices by Addiction Consult Services. JAMA Netw Open. 2025;8(8):e2526077. doi:10.1001/jamanetworkopen.2025.26077
- Crotty K, Freedman KI, Kampman KM. Executive Summary of the Focused Update of the ASAM National Practice Guideline for the Treatment of Opioid Use Disorder. J Addict Med. 2020;14(2):99-112. doi:10.1097/ADM.0000000000000635
- Englander H, Thakrar AP, Bagley SM, Rolley T, Dong K, Hyshka E. Caring for Hospitalized Adults With Opioid Use Disorder in the Era of Fentanyl: A Review. JAMA Intern Med. 2024;184(6):691-701. doi:10.1001/jamainternmed.2023.7282
- Garg R, Luo J, Bozinoff N, et al. Initiation and Dose of Methadone Monotherapy vs Combination Therapy, 2015 to 2023. JAMA Netw Open. 2025;8(8):e2527290. Published 2025 Aug 1. doi:10.1001/jamanetworkopen.2025.27290
- Huo S, Heil J, Salzman MS, Carroll G, Haroz R. Methadone initiation in the emergency department for opioid use disorder: a case series. J Emerg Med. 2023;64(3):391-396. doi:10.1016/j.jemermed.2023.01.012
- McCarthy, J. J., Leamon, M. H., Parr, M. S., & Anania, B. (2005). High-dose methadone maintenance in pregnancy: maternal and neonatal outcomes. American journal of obstetrics and gynecology, 193(3 Pt 1), 606–610.
- Meredith RR, Garneau WM, Feder KA, Buresh ME. Methadone Dose and Patient-Directed Discharge in Hospitalized Patients With Opioid Use Disorder. JAMA Netw Open. 2026;9(3):e263439. doi:10.1001/jamanetworkopen.2026.3439
- Nacev EC, Prewitt KC, Yang WT, et al. Feasibility of an Inpatient Split-Dose Rapid Methadone Induction Protocol for Pregnant Individuals. J Addict Med. Published online August 1, 2025. doi:10.1097/ADM.0000000000001548
- Khan NZ, Hand DJ, Qian E, et al. Split-dosing of Methadone During Pregnancy and Postpartum Period: A Systematic Review of Outcomes. J Addict Med. 2025;19(4):358-364. doi:10.1097/ADM.0000000000001470
- Racha S, Patel SM, Bou Harfouch LT, Berger O, Buresh ME. Safety of rapid inpatient methadone initiation protocol: a retrospective cohort study. J Subst Use Addict Treat. 2023;148:209004. doi:10.1016/j.josat.2023.209004
- Rückert-Eheberg IM, Steger A, Müller A, et al. Respiratory rate and its associations with disease and lifestyle factors in the general population - results from the KORA-FF4 study. PLoS One. 2025;20(3):e0318502. Published 2025 Mar 11. doi:10.1371/journal.pone.0318502
- Schoenfeld EM, Westafer LM, Beck SA, et al. "Just give them a choice": patients' perspectives on starting medications for opioid use disorder in the ED. Acad Emerg Med. 2022;29(8):928-943. doi:10.1111/acem.14507
- Schuckit MA. Treatment of Opioid-Use Disorders. N Engl J Med. 2016;375(4):357-368. doi:10.1056/NEJMra1604339
- Volkow ND, Jones EB, Einstein EB, Wargo EM. Prevention and Treatment of Opioid Misuse and Addiction: A Review. JAMA Psychiatry. 2019;76(2):208-216. doi:10.1001/jamapsychiatry.2018.3126
- Washington State Department of Children, Youth, and Families. Plan of safe care: healthcare providers. DCYF website. Accessed August 14, 2025. https://www.dcyf.wa.gov/safety/plan-safe-care/Healthcare-Providers


